Lentigo solaris, also known as a solar lentigo or sun spot, is a common, usually benign, flat brown patch on the skin that develops after long-term exposure to ultraviolet radiation. It most often appears on the face, backs of the hands, forearms, shoulders, neck and décolletage.
A typical lentigo solaris is not skin cancer and usually does not turn into cancer. However, not every brown spot on the skin is a harmless sun-induced pigmented spot. If a spot changes, becomes asymmetrical, multicoloured, bleeds, ulcerates, hurts, itches or looks different from other skin lesions, it should be examined by a dermatologist.
What is lentigo solaris?
Lentigo solaris, or solar lentigo, is a benign pigmented lesion in which more melanin accumulates in the upper layer of the skin. Melanin is the pigment that gives skin its colour and plays a role in the skin’s response to UV radiation.
This condition is also commonly called:
- a solar lentigo;
- a sun spot;
- an age spot;
- a brown pigmented spot on the skin.
The term “age spot” is not entirely precise. These spots do become more common with age, but the main cause is not age itself. It is the accumulated exposure to sunlight and other sources of UV radiation over a lifetime.
Why do sun spots develop?
The main cause is long-term exposure to ultraviolet radiation. UVA radiation penetrates deeper into the skin and contributes to photoageing, while UVB radiation mainly affects the upper layers of the skin and causes sunburn. Both types of radiation can influence pigmentation processes.
Under the influence of UV radiation, melanocytes, the cells that produce melanin, begin to work unevenly. In some areas, more pigment accumulates, and over time this becomes visible as a flat brownish spot.
Risk factors
- long-term sun exposure;
- repeated sunburns;
- use of tanning beds;
- fair skin phototype;
- outdoor work or hobbies;
- insufficient use of SPF;
- age and accumulated UV exposure;
- previous signs of sun damage on the skin.
What does lentigo solaris look like?
A typical lentigo solaris is a flat, light brown, tan or dark brown patch. It may be round, oval or slightly irregular in shape. The surface is usually smooth, without scaling, bleeding or ulceration.

The image shows typical solar lentigines on the skin of the hand: flat brownish patches in an area commonly exposed to sunlight over a lifetime.
On lighter skin, the spot often appears as a clearly visible brownish area. On darker skin, it may be dark brown or greyish brown and can sometimes be more difficult to distinguish from other forms of hyperpigmentation.
Common locations
- face;
- backs of the hands;
- forearms;
- shoulders;
- neck;
- décolletage;
- upper back;
- lower legs.
Is lentigo solaris dangerous?
A typical lentigo solaris is benign. It is usually not dangerous, not infectious and not skin cancer.
However, there are two important points:
- lentigo solaris shows that the skin has been exposed to UV radiation over a long period of time;
- some more serious skin lesions can look similar to a sun-induced pigmented spot.
Therefore, the key question is not only “is this pigmented spot dangerous?”, but also “is this spot really lentigo solaris?”. If there is any doubt, it is safer to consult a dermatologist.
When should a pigmented spot be shown to a dermatologist?
You should see a dermatologist if the spot:
- grows quickly;
- changes colour;
- becomes multicoloured;
- becomes asymmetrical;
- develops very irregular borders;
- bleeds, ulcerates, hurts or itches;
- becomes raised, rough or scaly;
- looks different from other skin lesions;
- appears as a new atypical pigmented lesion in adulthood.
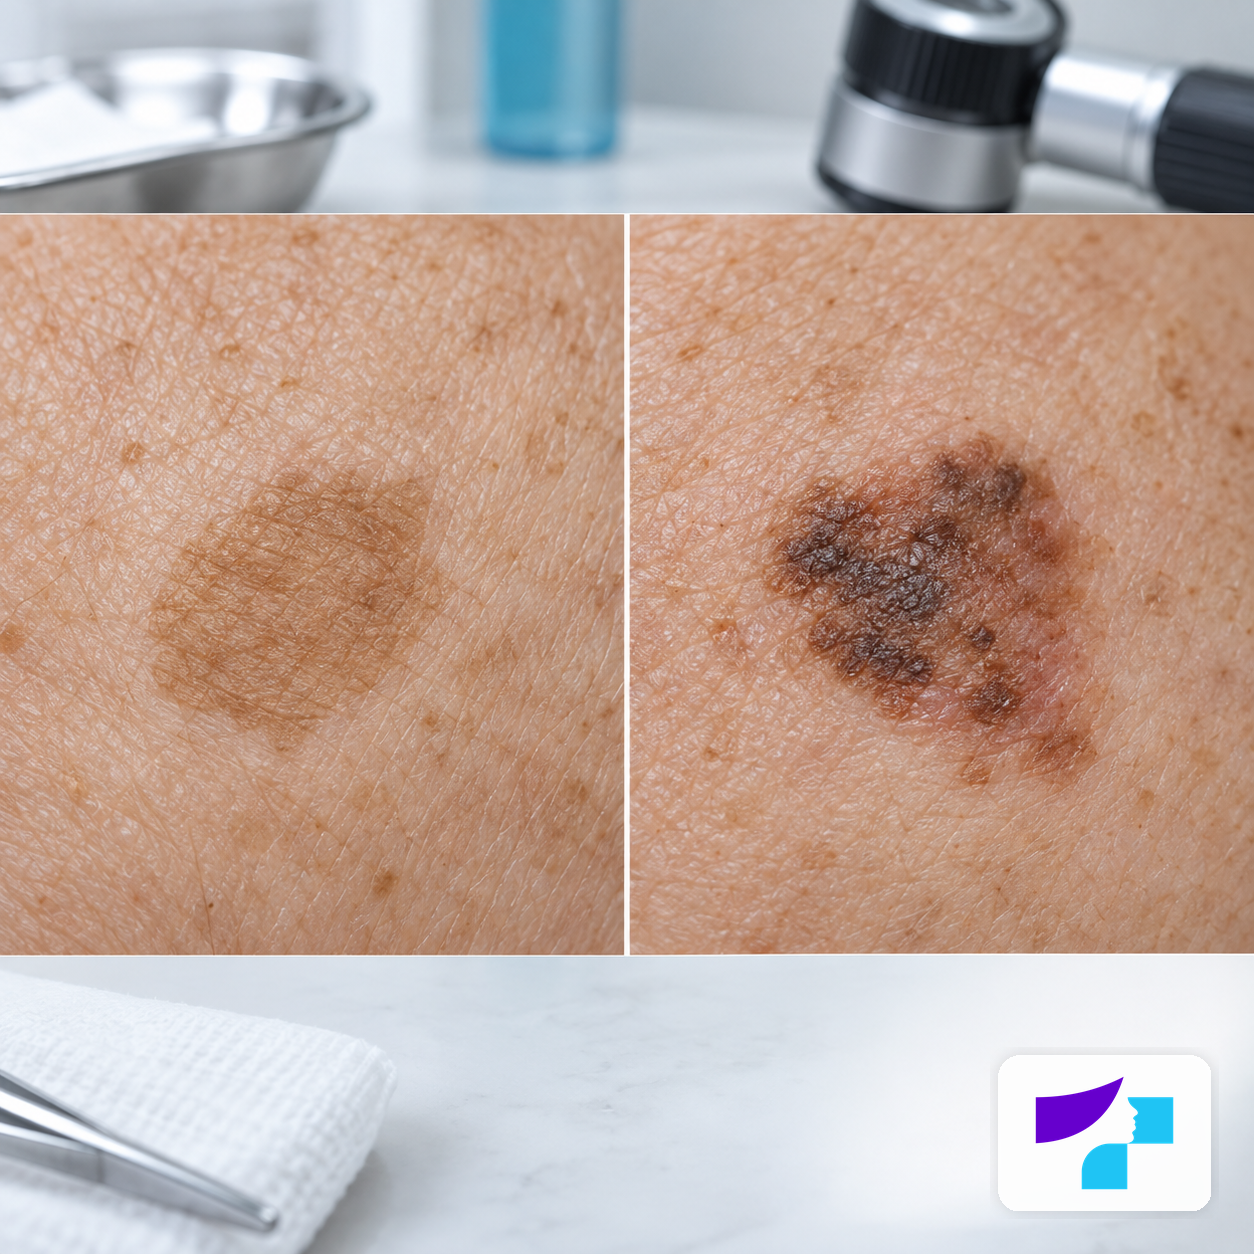
The image compares a calm, even solar lentigo with a pigmented lesion that has more irregular colour and borders. Such changes are a reason for dermatologist assessment, not self-diagnosis.
It is especially important to check pigmented spots before bleaching, laser treatment or other cosmetic procedures.
How can a sun spot be distinguished from melanoma?
It is not possible to make a reliable diagnosis at home, but the ABCDE rule can help identify warning signs that require medical assessment.
| Criterion | What to look for |
|---|---|
| A - asymmetry | One half of the spot looks different from the other. |
| B - border | The edges are jagged, blurred or very irregular. |
| C - colour | The spot contains several colours. |
| D - diameter | The spot is larger than 6 mm or continues to grow. |
| E - evolution | The spot changes over time. |
The “ugly duckling” sign is also useful: if one lesion looks different from all the others on the skin, it should be shown to a doctor.
What can lentigo solaris be confused with?
| Condition | Typical appearance | Main difference |
|---|---|---|
| Lentigo solaris | Flat brown spot. | Associated with chronic UV exposure. |
| Freckles | Small light brown dots. | Become more noticeable in the sun and may fade in winter. |
| Melasma | Larger symmetrical brown patches. | Often linked to hormones and UV radiation. |
| Mole | Flat or raised pigmented lesion. | Formed by a cluster of melanocytes. |
| Seborrhoeic keratosis | Rough, waxy, “stuck-on” plaque. | Often raised above the skin surface. |
| Actinic keratosis | Rough, scaly patch. | A precancerous lesion that should be assessed by a doctor. |
| Lentigo maligna | Irregular, slowly enlarging pigmented patch. | A form of melanoma in situ. |
| Post-inflammatory hyperpigmentation | Darker area after inflammation. | Appears after acne, trauma or a procedure. |
How does a doctor diagnose lentigo solaris?
A dermatologist assesses the spot’s shape, colour, borders, surface, size, location and changes over time. Dermoscopy is often used - an examination of the skin with a special magnifying device.
If the spot is typical, the diagnosis can often be made through examination and dermoscopy. If there is uncertainty about lentigo maligna, melanoma, pigmented actinic keratosis or another diagnosis, the doctor may recommend a biopsy. A biopsy means that a small tissue sample is examined in a laboratory.
In dermatopathology, lentigo solaris is usually characterised by increased pigmentation in the basal layer of the epidermis, signs of sun damage and changes in the structure of the epidermis. This information is mainly relevant to doctors rather than everyday self-monitoring.
Do sun spots disappear on their own?
Lentigo solaris usually does not disappear completely on its own. It may become lighter if the skin is consistently protected from the sun, but in summer or after UV exposure the spot may darken again.
Even after procedures, pigmented spots may return if sun protection is not maintained.
How is lentigo solaris treated or cosmetically reduced?
If lentigo solaris is benign and does not bother the patient, treatment is not necessary. If the spot causes cosmetic concern, options should be discussed with a dermatologist.
| Method | Potential benefit | Limitations |
|---|---|---|
| SPF and sun protection | Helps prevent darkening and new spots. | Usually does not completely remove an existing spot. |
| Retinoids | Support skin renewal. | Effect is gradual and irritation may occur. |
| Vitamin C | May improve overall skin tone. | Does not always significantly affect lentigo. |
| Azelaic acid | May help with hyperpigmentation. | Requires regular use. |
| Hydroquinone or other prescription agents | May reduce pigment. | Should be used under medical supervision. |
| IPL | May reduce more widespread pigmentation. | Not suitable for all skin types. |
| Pigment lasers | Often effective for individual spots. | Recurrence or side effects are possible. |
| Chemical peels | May reduce superficial pigmentation. | Risk of irritation and hyperpigmentation. |
| Cryotherapy | May help with individual spots. | A lighter patch or scar may occur. |
Clinical reviews suggest that different laser methods are often effective in reducing solar lentigines, but results vary and more high-quality comparative studies are still needed. Therefore, it is not appropriate to promise complete or permanent removal of pigmented spots.
Risks of procedures
Treating pigmented spots is not simply a cosmetic “bleaching” issue. An incorrectly chosen method may cause complications.
Possible risks include:
- post-inflammatory hyperpigmentation;
- hypopigmentation, or a lighter patch;
- redness;
- crusting;
- skin irritation;
- scarring;
- incomplete effect;
- return of pigmentation.
These risks may be higher in darker skin phototypes, so procedures should be planned with particular care.
SPF and prevention
Sun protection is the most important prevention. It helps prevent new pigmented spots and reduces darkening of existing ones.

The image shows daily sun protection: applying SPF to the skin, together with a hat and sunglasses. These habits help reduce new solar lentigines and prevent existing spots from becoming darker.
Recommended measures:
- use a broad-spectrum SPF 30 or SPF 50 sunscreen;
- apply enough sunscreen;
- reapply every 2 hours when outdoors;
- wear a wide-brimmed hat;
- choose protective clothing;
- avoid intense midday sun;
- do not use tanning beds.
For facial pigmentation, SPF 50 is often a practical choice. Some people may also benefit from tinted sunscreens containing iron oxides, as they help protect against the effects of visible light as well.
What should not be done?
You should not:
- burn, scratch or injure the spot yourself;
- use acids or bleaching agents without a diagnosis;
- bleach a spot that is changing or looks atypical;
- rely only on pictures found online;
- use tanning beds to “even out” skin tone;
- delay a visit if the spot bleeds, ulcerates or grows.
How to monitor pigmented spots?
Examine your skin once a month in good light. Photograph the spot if it seems new or changing. Write down the date and approximate size. Observe the colour, borders, shape, surface and symptoms.
If there are many pigmented lesions on the skin, a family history of melanoma or previous skin cancer, a dermatologist may recommend regular skin checks or digital dermoscopy.
Common myths
Myth: a sun spot always means skin cancer
Fact: a typical lentigo solaris is benign.
Myth: a sun spot always turns into melanoma
Fact: a typical lentigo solaris usually does not turn into melanoma, but lentigo maligna can look similar.
Myth: vitamin C completely removes pigmented spots
Fact: it may help improve skin tone, but it does not guarantee that the spot will disappear.
Myth: laser treatment always solves the problem permanently
Fact: results may be good, but pigmentation can recur.
Myth: SPF is needed only in summer
Fact: UV radiation affects the skin in spring, autumn and bright winter days as well.
Myth: tanning beds are safer than the sun
Fact: tanning beds are a source of UV radiation and damage the skin.
Summary
Lentigo solaris, or a sun-induced pigmented spot, is a common, usually benign brown patch caused by long-term exposure to UV radiation. It most often appears on the face, hands, neck, shoulders and décolletage. Treatment is not necessary if the spot is benign and not bothersome, but cosmetic reduction is possible with topical agents, laser therapy, IPL, peels or other methods. Before any treatment, it is important to make sure that the spot is not suspicious.
Medical disclaimer
This information is educational and does not replace a dermatologist consultation, diagnosis or treatment. Any new, changing, bleeding, ulcerating, painful, itchy, asymmetrical or multicoloured pigmented skin lesion should be examined by a dermatologist. Do not attempt to bleach, burn or treat pigmented spots yourself with unverified products.
References and authoritative sources
- DermNet: solar lentigo
- Pathology Outlines: dermatopathological features of solar lentigo
- PubMed Central: systematic review of treatment methods for solar lentigines
- Sundhed.dk: clinical handbook on lentigo solaris
- Actas Dermo-Sifiliográficas: differential diagnosis of solar lentigo and lentigo maligna
- American Academy of Dermatology: age spots and their treatment
- American Academy of Dermatology: how to choose sunscreen
- Cleveland Clinic: solar lentigines and age spots
- Centre for Disease Prevention and Control of Latvia: public health information
- Ministry of Health of the Republic of Latvia: healthcare information
